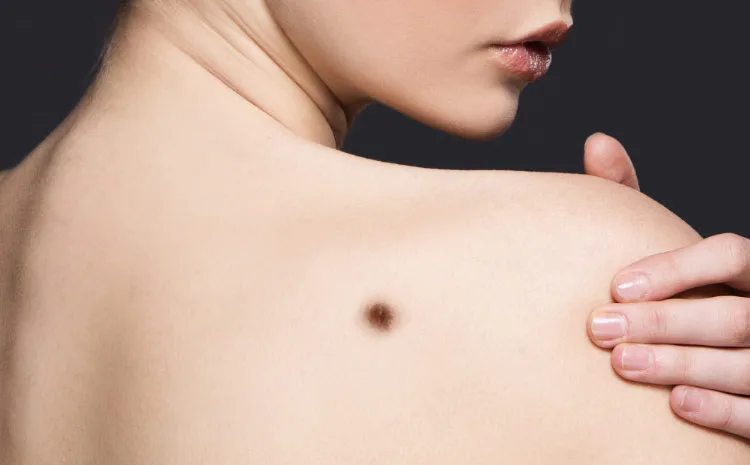
Precursors of cutaneous melanoma
Precursors of cutaneous melanoma
Dr Giuseppe Noto
Dermatologist, Palermo
About 75-80% of cutaneous melanomas would form directly on healthy skin, so only 20-25 % of melanomas would arise on a skin lesion that we can identify as a clinical precursor.
It remains to be established whether these so-called precursors should be considered precancerous lesions, or whether onset on a naevus is rather the result of a merely statistical percentage, since naevi are melanocytic aggregates, and the risk of developing a melanoma is in all probability genetically determined, and therefore theoretically inherent in the skin as a whole, amplified by certain environmental factors.
A different problem is posed by the rare circumstances in which a cutaneous melanoma arises on skin whose ability to repair photoinduced damage is genetically altered, as in the case of xeroderma pigmentosum, with an incidence about 2000 times higher (1), or in the case of genetic or acquired immunodeficiency, as with immunosuppression in organ transplant recipients (2) or in people with Hodgkin's lymphoma (3). We can identify three large groups of pigmented skin lesions that may be regarded as possible precursors of melanoma: a) congenital melanocytic naevi, b) dysplastic or atypical naevi, c) acquired melanocytic naevi. The aim is to try to clarify what clinical relevance the so-called precursors of melanoma have and, above all, what clinical approach is most appropriate for each group. Congenital melanocytic naeviThe most classic and obvious definition of a congenital naevus might be "a melanocytic naevus present at birth"; however, some lesions with the clinicopathological features of a congenital naevus can also develop during early childhood. The clinicopathological features that allow a congenital naevus to be diagnosed are the presence of brownish pigmented skin lesions, macular or plaque-like, often with hair activation, conventionally divided into small (20cm), characterised by the presence of melanocytes in the lower two thirds of the dermis, with occasional extension to the subcutaneous tissue, with cells, isolated or in rows, between the collagen fibres of the reticular dermis, and with a tendency towards periadnexal, perineural and perivascular arrangement. However, some congenital naevi do not show these histopathological features; this occurs in particular with small congenital naevi and in an undefined percentage of medium-sized congenital naevi. This clinicopathological discordance could lead to discrepancies in studies aimed at establishing the degree of precancerousness of congenital naevi when they are conducted exclusively on a histopathological basis. A problem that is still open is defining the risk of melanoma associated with a congenital naevus. In 1982 (4) a study found a 21-fold higher risk of melanoma in people with a congenital naevus diagnosed clinically and from their medical history, while the risk would be "only" 3 to 10 times higher when the naevi are diagnosed on the basis of histological parameters. Others (5) had previously shown that the reliability of the questionnaire completed by parents leaves much to be desired and only a third of the lesions described as congenital naevi proved to be so on the basis of histological parameters. In addition, a rate of 8.1% of melanomas histologically associated with naevi with the histological features of a congenital naevus was described (4), an association 8 times higher than that found by others (6). In another assessment (7) of 48 congenital naevi with a diameter of less than 10 cm, only two cases showed naevus cells in the lower third of the dermis or in the subcutaneous tissue. The melanomas on congenital naevi that were studied were of junctional origin and all formed after the age of 18. None of these melanomas showed the neuromesenchymal features frequently observed in melanoma associated with giant congenital naevi. Indeed, the "non-epidermal" onset of a melanoma on a small congenital naevus is to be considered exceptional (8,9), unlike what happens with giant congenital naevi. In another cohort study of 265 cases (10), the risk of melanoma in people with congenital naevi was assessed: in the 232 cases with a congenital naevus covering less than 5% of the body surface no melanomas were observed, while in 2/33 cases with involvement >5% two fatal melanomas were observed. In another clinical assessment (11) of 230 medium-sized congenital naevi followed up to an average age of 26, no melanoma was observed. By contrast, in giant congenital naevi the risk of melanoma has been estimated at between 5% and 20% (12). In another study (13), 46 cases of giant congenital naevus were followed and the cumulative risk of melanoma was found to be 5.7%. The melanocytic neoplasm arising on a giant congenital naevus frequently has a heterogeneous morphology resulting from the transformation of neural crest cells in a heterotopic site, probably due to altered migration during the embryonic phase (14). There is also a risk of extracutaneous melanoma, in particular leptomeningeal, in people with neurocutaneous melanosis. It should also be stressed that about 60% of melanomas that develop on giant congenital naevi occur in the first decade of life, in particular in the first 5 years (15). Another problem is that, since about two thirds of melanomas on giant congenital naevi are of "non-epidermal" origin (16), clinical and dermoscopic observation revealing a "junctional" melanoma does not help us with early diagnosis, as it does for superficial spreading melanoma. Conversely, in small congenital naevi melanoma can arise, as happens in acquired melanocytic naevi, at junctional level with a risk that appears to be extremely low, so prophylactic excision should not be immediately indicated. If surgery is considered appropriate, it can be carried out around the age of puberty, because malignant transformation before puberty is an exceptional event. By contrast, in giant congenital naevi, given the high propensity for neural crest neoplasms to arise, excision (often not easy) is recommended at a young age. In these cases it should be noted that extending the surgery down to the fascia does not fully guarantee radical removal, precisely because primordial neural crest cells can remain in the deep tissues (17). In medium-sized congenital naevi, the precancerous potential could depend on the histopathological pattern of the lesion rather than on the size of the naevus. A good proportion of these "intermediate" naevi, as is observed with small congenital naevi, may not have melanocytes in the deep dermis. So a small incisional punch biopsy on medium-sized congenital naevi could allow a better prognostic classification. Dysplastic naevi or atypical naeviThe dysplastic naevus was noted and described in 1978 in 6 families with melanoma (18). These naevi showed variability in shape, colour and size. They were located mainly on the upper part of the trunk and on the extremities, were numerous in each individual, and the families with members in whom these naevi were observed had a high incidence of melanoma. Subsequently this condition has been described under various names, namely dysplastic naevus syndrome, familial atypical mole syndrome and melanoma syndrome (19-21). Dysplastic naevi can be observed in people with or without melanoma and can be familial or occur sporadically. As a rule they are larger than 5 mm and look flat or have a raised centre. The colour is dark or in any case irregularly pigmented. They are quite common, accounting for about 5% of skin histopathology reports (22). Clinically, dysplastic naevi differ from acquired naevi in that they appear around puberty or even during childhood>, showing dynamic behaviour during adult life, and also in that they continue to develop throughout life, even beyond the fourth decade. The histopathological criteria for diagnosing a dysplastic naevus are less clear-cut than the clinical ones. A consensus conference (20) defined as criteria the presence of architectural disorder with asymmetry, subepidermal fibroplasia (concentric or lamellar), and lentiginous melanocytic hyperplasia with spindle or epithelioid cells aggregated in nests of irregular shape and size, with bridging between the rete ridges of the epidermis. Cytological atypia of the melanocytes may be present to a variable degree, and a lymphomonocytic infiltrate may also be observed in the superficial dermis. The syndrome was defined as "familial atypical multiple mole melanoma syndrome", with melanoma in one or more first- or second-degree blood relatives, a large number of melanocytic naevi with an atypical clinical appearance, often more than 50, and the histopathological features of a dysplastic naevus. Today the clinical evidence for familial dysplastic naevus syndrome is no longer in doubt. The risk of developing melanoma would be 184 times higher in people with familial dysplastic naevi but no family history of melanoma, while it would be 500 times higher in people with both familial dysplastic naevi and a family history of melanoma (21). People with sporadic non-familial dysplastic naevi have been included by some authors among individuals with an increased risk of melanoma, though at much lower levels than people with familial dysplastic naevi (23). As the number of dysplastic naevi in the same person increases, the related risk of melanoma would also increase (24,25). A major nosological problem with the concept of the non-familial dysplastic naevus is the clinico-histological correlation, which is often inconsistent: in other words, it is possible to observe a clinically dysplastic naevus that then turns out to be histologically normal, and vice versa. So the ability to predict histological dysplasia on a clinical basis is quite limited (26). In one study, of 91 clinically dysplastic naevi only 23 showed histological dysplasia (27). In another assessment, using the histological criteria for diagnosing dysplastic naevi as objectively as possible, an incidence of 53% was paradoxically established in white people (28). It is therefore important to distinguish the familial form of dysplastic naevus, which is a strong risk factor for melanoma, from the non-familial dysplastic naevus, which can be observed in sporadic form and in which the risk of melanoma would depend on the total number of melanocytic naevi, the phototype and environmental factors. Acquired melanocytic naeviCommon flat melanocytic naevi consist of aggregates of naevus (or melanocytic) cells which, in the great majority of the white population, appear as small skin macules a few millimetres in diameter, varying in colour from light brown to dark brown. Apart from the common flat melanocytic naevus, acquired melanocytic naevi with particular features in white people can be defined, drawing on a well-known and simple eponymous classification, as Clark, Unna, Miescher, Spitz and Reed naevi (29). Histologically, melanocytic naevi are classified as junctional (nests at the tips of the rete ridges composed of melanocytic aggregates), intradermal (regular cords of naevus cells in the dermis with progressive maturation in depth), compound (with both components) and lentiginous (with regular epidermal hyperplasia). Apart from small common flat pigmented naevi, Clark naevi make up the great majority of acquired melanocytic naevi; they appear as macular or maculopapular growths or small brownish plaques that are fairly symmetrical, round or oval in shape and sometimes slightly irregular, with a smooth surface that is barely or not at all palpable or is raised in the centre of the lesion, and a diameter ranging from a few millimetres up to a centimetre; in Clark naevi it is possible to observe small regressive areas that look regular and are limited in extent compared with the total area of the naevus. Unna naevi appear as lesions of a few millimetres, exophytic and brownish, with a sessile or pedunculated base, soft consistency and smooth surface. Miescher naevi appear as papular lesions of a few millimetres, brownish or skin-coloured, dome-shaped with a smooth surface and regular borders, generally located on the face. Spitz naevi generally arise during childhood, are frequently located on the face and appear in hypochromic form as red or pinkish-brown papular lesions with a smooth surface and regular margins; histologically they show epithelioid or spindle melanocytes, poorly pigmented, aggregated in vertically arranged oblong nests or clusters with hyperplastic epidermal hyperplasia and typical clefts; small eosinophilic globules (Kamino bodies), remnants of basement membrane, may be observed; the melanocytes can extend deep into the dermis with maturation, and the inflammation, when present, is fairly regularly arranged. Reed naevi, considered by some to be a pigmented, spindle-cell variant of Spitz naevi, appear as intensely pigmented, symmetrical plaque-like or papular lesions, often arising in young adults, particularly on the limbs, barely palpable, with margins that are not always regular and a characteristic dermoscopic pattern with radiating pseudopods; it is current opinion, though we do not know how justified, to surgically remove Reed naevi after puberty. The blue naevus appears as a plaque-like, papular or nodular lesion, frequently located on the backs of the hands and feet, of a uniform bluish colour and smooth surface, formed by dendritic melanocytes located in the dermis accompanied by occasional melanophages and fibrotic stroma. The so-called malignant blue naevus is a rare melanoma arising in the context of a blue naevus. Other clinical aspects of naevus growths should be mentioned, such as Sutton's naevus or halo naevus (round perilesional achromia), Meyerson's naevus (with a spongiotic inflammatory reaction) and Barr's naevus (with a desmoplastic histological appearance). Acquired melanocytic naevi generally appear after the first year of life and can increase in number and size during and even after somatic growth, normally not exceeding 5 mm in diameter (23). Only 20% of adults would have no common flat naevi and Clark naevi larger than 2 mm (30). It is likely that the presence of acquired melanocytic naevi in every population is determined by genetic, environmental and probably immunological factors (31), and this occurs more in areas exposed to the sun or to sunburn (32). It has been found that people with more than 50 melanocytic naevi would have an increased relative risk of melanoma, quantified at 12.1 in the absence of clinical criteria for dysplastic or atypical naevi, while in individuals with clinically atypical naevi, in other words with a diameter greater than 7 mm, irregular margins and uneven colour, the relative risk of melanoma would rise to 54 (30). In another assessment, people with between 50 and 100 naevi had a relative risk of melanoma of 3.2 compared with a control group made up of individuals with between 0 and 4 naevi. People with more than 100 naevi had a risk of 7.7 (33). In another study, the relative risk of melanoma in central Europe in people with more than 50 naevi was quantified at 14.9 (34). According to another investigation (35), the relative risk of melanoma would not depend on the presence or absence of clinically atypical naevi but only on the total number of Clark naevi; people with more than 120 naevi had a risk of 19.6, and patients with naevi in photoprotected areas formed a higher-risk subgroup. The ages at which screening for melanoma seems most important are middle and old age (36). It can therefore be reliably argued that a large number of Clark naevi is a risk factor for cutaneous melanoma in white people. One possible current explanation for this could lie in the fact that a person with many naevi, having a greater number of naevus cells, or melanocytes, also has a greater probability of developing a melanoma. On the other hand, there is the objective fact that the great majority of melanomas (75-80%) arise on healthy skin, so the expression of numerous Clark naevi could simply be one aspect of the phenotype of a person whose skin has a higher relative risk of melanoma, a risk that is genetically determined and jointly influenced by environmental factors.
Bibliography:
1) Kraemer KH, Lee MM, Scotto J. Xeroderma pigmentosum: cutaneous, ocular and neurologic abnormalities in 830 published cases. Arch Dermatol 1987;123:241-50.
2) Greene MH, Young TL, Clark WH Jr. Malignant melanoma in renal transplant recipients. Lancet 1981;1:1196-9.
3) Tucker MA, Misfeldt D, Coleman N et al. Cutaneous malignant melanoma after Hodgkin’s disease. Ann Intern Med 1983;102:37-41.
4) Rhodes AR, Melski JW. Small congenital nevocellular nevi and the risk of cutaneous melanoma. J Pediatr 1982;100:219-24.
5) Walton RG, Jacobs AH, Con AJ. Pigmented lesions in newborn infants. Br J Dermatol, 1976;95:389-96
6) Kopf AW, Barb RS, Hennessey P. Congenital nevocytic nevi in malignant melanoma. J Am Acad Dermatol 1979;1:123-4.
7) Illig L, Waidner F, Hundeiker M et al. Congenital nevi 10cm as precursors to melanoma. Arch Dermatol 1985;121:1274-81.
8) Sharpe RJ, Salasche SJ, Barnhill RL, Sober AJ. Non-epidermal origin of cutaneous melanoma in a small congenital nevus. Arch Dermatol 1990;126:1559-61.
9) Paull WH, Polley D, Fitzpatrick JE. Malignant melanoma arising intradermally in a small congenital nevus of an adult. J Dermatol Surg Oncol 1986;12:1176-8.
10) Swerdlow AJ, English JSC, Qiao Z. The risk of melanoma in patients with congenital nevi: a cohort study. J Am Acad Dermatol 1995;32:595-9.
11) Sahin S, Levine L, Kopf AW et al. Risk of melanoma in medium-sized congenital melanocytic nevi: a follow-up study. J Am Acad Dermatol 1998;39:428-33.
12) Consensus conference on precursors of melanoma. JAMA 1984;251:1864-6.
13) Egan CL, Oliveira SA, Elenitsas R et al. Cutaneous melanoma risk and phenotype changes in large congenital nevi: a follow-up study of 46 patients. J Am Acad Dermatol 1998;39:923-32.
14) Jerdan MS, Cohen BA, Smith RRL, Hood AF. Neuroextradermal neoplasms arising in congenital nevi. Am J Dermatopathol 1985;7(suppl):41-8.
15) Kaplan EN. The risk of malignancy in large congenital nevi. Plast Reconstr Surg 1974;53:421-8.
16) Rhodes AR, Wood WC, Sober AJ, Mihm MC. Non-epidermal origin of malignant melanoma associated with giant congenital nevocellular nevus. Plast Reconstr Surg 1981;67:782-90.
17) Ruiz Maldonado R, Orozco-Covarrubias ML. Malignant melanoma in children: a review. Arch Dermatol 1997;133:363-71.
18) Clark WH Jr, Reimer RP, Greene M et al. Origin of familial malignant melanomas from heritable melanocytic lesions: the B-K mole syndrome. Arch Dermatol 1978;114:732-8.
19) Greene MH, Clark WH Jr, Tucker MA et al. Precursor naevi in cutaneous malignant melanoma: a proposed nomenclature. Lancet 1980;2:1024.
20) Consensus development panel on early melanoma. Diagnosis and treatment of early melanoma. JAMA 1992;268:1314-9.
21) Greene MH, Clark WH Jr, Tucker MA et al. The prospective diagnosis of malignant melanoma in a population at high risk: hereditary melanoma and the dysplastic nevus syndrome. Ann Intern Med 1985;102:458-65.
22) Crutcher WA, Sagebiel RW. Prevalence of dysplastic nevi in a community practice. Lancet 1984;1:729.
23) Rhodes AR, Weinstock MA, Fitzpatrick TB et al. Risk factors for cutaneous melanoma. JAMA 1987;258:3146-54.
24) Bataille V, Bishop JA, Sasieni P et al. Risks of cutaneous melanoma in relation to the numbers, types, and sites of naevi: a case-control study. Br J Cancer 1996;73:1605-11.
25) Tucker MA, Halpern A, Holly EA et al. Clinically recognized dysplastic nevi: a central risk factor for cutaneous melanoma. JAMA 1997;277:1439-44.
26) Annessi G, Cattaruzza MS, Abeni D et al. Correlation between clinical atypia and histological dysplasia in acquired melanocytic nevi. J Am Acad Dermatol 2001;45:77-85.
27) Roush GC, Dubin N, Barnhill RL. Prediction of historical melanocytic dysplasia from clinical observation. J Am Acad Dermatol 1993;4:555-62.
28) Piepkorn M, Meyer LJ, Goldgar D et al. The dysplastic melanoma nevus: a prevalent lesion that correlates poorly with clinical phenotype. J Am Acad Dermatol 1989;20:407-15.
29) Ackerman AB, Magana-Garcia M, Di Leonardo M. Naming acquired melanocytic nevi: Unna’s, Miescher’s, Spitz’s, Clark’s. Am J Dermatopathol 1990;12:193-209.
30) Swerdlow AJ, English J, MacKie RM. Benign melanocyte nevi as a risk factor for malignant melanoma. BMJ 1986;292:1555-9.
31) Williams ML, Pennella R. Melanoma, melanocyte nevi and other melanoma risk factors in children. J Pediatr 1994;124:833-45.
32) Gallagher RP, McLean DI, Yang CP et al. Anatomic distribution of acquired melanocyte nevi in white children. Arch Dermatol 1990;126:466-71.
33) Bataille V, Bishop JA, Sasieni P et al. Risks of cutaneous melanoma in relation to the numbers, types, and sites of naevi: a case-control study. Br J Cancer 1996;73:1605-11.
34) Weiss J, Bertz J, Jing EG. Malignant melanoma in southern Germany: different predictive value of risk factors for melanoma subtypes. Dermatologica 1991;183:109-13.
35) Grob H, Gouvernet J, Aymar D et al. Count of benign melanocytic nevi as a major indicator of risk for nonfamilial nodular and superficial spreading melanoma. Cancer 1990;66:387-95.
36) Geller AG, Gilchrest B, Miller D, et al. Should mass screening for skin cancer be targeted to middle-aged and older men? Findings from the United States. Melanoma Res 2001;11(suppl 1):150-1.
For any reports or complaints, please contact the owner of this website at the email address gdtif@gditalia.biz
